In March and April, we ran two workshops and brought together thirteen people at different stages of their consumer representation journeys. What they shared was honest, thoughtful and consistent with what we have heard over many years of running this training.
People come to this work because something happened to them or to someone they love, and they want it to mean something changes for the next person. They want to understand the system well enough to push back on it. They want to contribute in a way that is heard and respected, not just invited in and then overlooked.
“our perspectives and experiences are so valuable and give services and systems the information they can’t get anywhere else”
We have put together a full summary of both workshops, including what participants told us about the value of lived experience, the realities of consumer representative roles, the importance of diversity and who is still missing from these spaces, and what makes participation meaningful rather than tokenistic.
Why this matters beyond the training room
Consumer representatives play a specific and important role in systems change. They bring the perspectives of people who use services into the places where decisions are made. They help ensure that what the health system understands about what is working, what is missing and what needs to change is grounded in real life, not just data and projections.
HCCWA’s role is to make sure the people stepping into those roles feel ready: informed, supported and clear that their experience is a form of expertise. That has been our commitment for 34 years and this training is one of the places where that commitment shows up in practice
A training built for the long haul
This is not a one-off workshop or a box to tick before someone is assigned to a committee or a working group or a seat at an executive table. It is a space where people with lived and learned experience of health services can explore what consumer representative work actually involves, think about whether and how they want to contribute, and build confidence to do that well. The content covers the shape of the WA health system and where consumer voices can fit within it. It is honest about the challenges: the risk of tokenism, the emotional weight of bringing personal experience into formal spaces, the patience required when change is slow. And it is grounded, always, in the belief that people who use health services hold knowledge the system cannot get from anywhere else.
It has been delivered face to face, fully online, and now in both formats because we have learned that different options open the door for different people. In 2026, two people who couldn’t make the Saturday in-person session came back and attended the Tuesday evening online session instead. That is what genuine accessibility looks like: not just saying people are welcome, but making sure there is more than one way in.
Over three decades of consumer voices: the training that keeps people ready
Since 1994, Health Consumers’ Council WA has stood alongside people who use health services across WA. Throughout that time, one thread has run consistently through our work: helping people understand that their experience matters, that their voice belongs in the room, and that they have something real to contribute to making the health system better.
Our Introduction to Consumer Representation training is one of the ways we do that. The current iteration of this training goes back to 2019, but this commitment goes back much further. The format has evolved; the purpose has not.
Read the full 2026 workshop summary report or get in touch with us at engagement@hconc.org.au if you are interested in consumer representation opportunities or want to know when our next session is running.
We’re excited to share HCCWA’s new Health Passport — a simple, practical tool designed to make healthcare appointments easier and less stressful for people from non-English speaking backgrounds.
The Health Passport helps people share important information with health services, especially when they are not yet confident reading or writing in English, or when they need communication support such as an Auslan interpreter.
With support from a family member, carer, community worker or service provider, a person can complete the Health Passport before attending a health appointment. Once completed, it gives healthcare staff key information at a glance, helping to reduce the need for people to repeatedly answer questions they may not fully understand or feel confident responding to.
We hope the Health Passport helps people feel more prepared, supported and confident when accessing care — and helps health services provide care that is respectful, inclusive and person-centred.
The Health Passport is now available to download and use. We encourage you to share it with your community, clients, networks and anyone who may find it helpful.
We warmly welcome feedback from both health consumers and healthcare providers as we continue working together to make healthcare more accessible for everyone.
This work also connects closely with HCCWA’s Diversity Dialogues initiative, which brings together consumers, carers, communities, and healthcare organisations to discuss how we can improve healthcare access and experiences for everyone in WA.
Our next Diversity Dialogues session will focus on improving access to care for older people from migrant and refugee backgrounds.
WA Health now has a mandatory policy for how body worn cameras can be used in public health facilities. The policy is intended to support safety during incidents of violence, aggression or threatening behaviour, while protecting people’s privacy, dignity and rights.
Plain language question
Plain language answer
Who can use body worn cameras?
Only Security Officers can use them under this policy.
When can they be turned on?
Only when there is an imminent safety risk involving violent, aggressive or threatening behaviour.
Are they for routine surveillance?
No. They must not be used for general monitoring, intimidation, harassment, discrimination, personal use or staff disputes.
Do people need to be told?
Yes, where practicable. Security Officers should clearly tell people the camera is being activated and that they are being recorded.
When should recording stop?
Recording should stop once the incident is resolved and the immediate safety risk has passed.
How is footage handled?
Footage must be downloaded, securely stored, linked to a security incident report, and accessed or disclosed only under relevant WA Health rules.
What the policy allows
Body worn cameras can only be used by Security Officers when they are responding to incidents involving violent, aggressive or threatening behaviour.
They are one part of a broader workplace violence and aggression response. The cameras may help deter or de-escalate behaviour and may create an objective record of an incident.
They must be used lawfully, ethically and proportionately.
What the policy does not allow
Cameras are not for routine or general surveillance.
They must not be used for personal purposes, staff disputes, intimidation, harassment or discrimination.
They should not be activated simply because a person is distressed, unwell, frustrated or upset unless there is an immediate safety risk involving threatening, violent or aggressive behaviour.
When cameras can be turned on
A camera can only be activated when there is an imminent risk to the safety of workers, patients or visitors.
Imminent risk means there is a credible and immediate threat based on current, clear and objective signs that harm is happening or about to happen.
Where practicable, Security Officers must tell people clearly that the camera is being turned on and that they are being recorded. This may include physical actions, such as pointing to the camera, to support understanding.
Places and situations needing extra care
Cameras should generally not be activated in highly private or sensitive spaces, such as toilets, change rooms, bathrooms, parent rooms, lactation rooms, clinical treatment areas, during medical procedures, or when someone is undressed.
The exception is where there is an imminent safety risk involving threatening, violent or aggressive behaviour.
Security Officers should consider relevant information from clinical staff before activating a camera, including known clinical conditions, substance use, triggers or behavioural history, particularly where recording may escalate the situation.
When recording must stop
Recording should stop once the incident has been resolved, the immediate safety risk has passed, and the Security Officer has been stood down from the incident or risk.
If a patient, carer, guardian, staff member or member of the public asks for recording to stop, the Security Officer must assess whether continued recording is still necessary and lawful.
If recording continues, the person should be told clearly.
Privacy and access to footage
Body worn cameras are treated as listening and optical surveillance devices under WA surveillance law.
Recordings must avoid unlawful recording of private conversations or private activities.
Footage must be downloaded and stored securely at the end of each shift, or as soon as practicable, in an access-controlled system.
Stored footage must be linked to a relevant security incident report. Access, use or disclosure must be managed under relevant WA Health information access, retention, privacy and Aboriginal data governance policies.
How use will be reported and monitored
The policy includes only limited requirements for reporting and monitoring body worn camera use.
When a workplace violence and aggression incident occurs and a camera is activated, the incident report must include the words “BWC activated” so footage can be linked to the incident record.
Footage must be linked to the relevant security incident report and stored in an access-controlled system.
Compliance monitoring focuses on whether Security Officers have completed mandatory body worn camera training.
The System Governance and Reform Unit, on behalf of the System Manager, may ask Health Service Providers for additional information to evaluate compliance and support policy evaluation.
The policy does not clearly set out routine public or consumer-facing reporting on how often cameras are used, where they are used, who is recorded, whether people ask for recording to stop, complaints about camera use, access requests, disclosures of footage, or audit outcomes.
Training and local procedures
Health Service Providers must develop their own procedures that align with the statewide policy.
Security Officers must complete training before wearing or operating a camera.
Training must cover legal requirements, activation and deactivation, access and disclosure, end-of-shift processes, incident reporting, verbal notification, camera positioning and device operation.
Consumer-rights and implementation issues to watch
Whether consumers, carers and visitors are told about camera use in clear, accessible and culturally safe ways.
How staff decide that a safety risk is imminent, and whether that decision is documented consistently.
How the policy is applied for people who are distressed, unwell, intoxicated, experiencing mental health crisis, cognitively impaired, neurodivergent, communicating in a language other than English, or experiencing cultural unsafety.
Whether recording in sensitive clinical or personal spaces is treated as genuinely exceptional.
How people can ask questions, raise concerns, make complaints or request access to information about footage involving them.
Whether local procedures include practical guidance for de-escalation, trauma-informed care, disability access, interpreter use, and culturally safe communication.
Whether local monitoring includes consumer-focused measures, such as number of activations, locations, reasons for activation, requests to stop recording, complaints, access requests, disclosures and equity impacts.
Note
This summary is intended to support discussion. It does not replace the official WA Health policy.
WA Health has introduced a statewide mandatory policy for body worn camera use in public health facilities. The policy is about staff and visitor safety, but it also raises important questions about trust, dignity, communication, privacy and accountability.
WA Health has introduced a new mandatory policy about the use of body worn cameras in public health facilities. The policy is focused on supporting safety during incidents involving violence, aggression or threatening behaviour. It sets out when body worn cameras can be used, who can use them, how people should be told they are being recorded, and how footage should be managed.
Health Consumers’ Council WA was invited to take part in the policy consultation process, alongside clinical, safety and health system representatives. We appreciated the opportunity to bring a consumer perspective into those discussions and to speak to what matters for people, families and communities when they are accessing care.
For us, this conversation was about more than the cameras themselves. It was about trust, dignity, communication, privacy and safety.
We also want to acknowledge why this policy exists. Health care workers, security staff and others working in our health system have the right to be safe at work. No one should experience violence, aggression, threats or abuse while providing care or supporting people in health services.
When staff feel unsafe, this can affect everyone – staff, patients, families, carers and other people nearby. A safer environment supports better care.
From a consumer perspective, supporting staff safety and protecting consumer rights are not opposing goals. Both matter. The important question is how safety measures are used, especially in situations where people may be unwell, frightened, distressed, overwhelmed or in crisis.
This is not completely new
Body worn cameras are already used in a range of public safety and frontline settings across Australia. They have also already been used in some WA health settings.
For example, WA Country Health Service has had a local Body Worn Camera Procedure for security officers working at WACHS health sites and facilities. That procedure was published in May 2025 and covers the use of body worn cameras, associated equipment, and the capture, management, storage, retrieval and release of digital data.
WACHS also has an Electronic Security Systems Policy that includes body worn cameras as part of its broader security arrangements, alongside CCTV, duress alarms and access or identification cards.
So, the new WA Health policy is not simply about introducing a new technology for the first time. What is new is the statewide mandatory policy. This creates a system-wide framework for the lawful, ethical and consistent use of body worn cameras across all WA public health facilities.
We have not found publicly available body worn camera-specific policies for every Health Service Provider. This is one reason a statewide policy matters: it gives services a shared set of minimum requirements, rather than relying only on local arrangements that may differ between services and may not be easy for consumers to find.
What the WA policy says
Under the WA Health policy, body worn cameras can only be used by Security Officers. They are not for routine surveillance. They may be activated only when there is an imminent risk to the safety of staff, patients or visitors because of violent, aggressive or threatening behaviour.
Where practicable, people should be told that recording is starting. This is important because clear communication can help reduce fear, confusion and mistrust, especially for people who may already be distressed or struggling to understand what is happening.
The policy also recognises that extra care is needed in private, sensitive and clinical areas. From a consumer perspective, this is one of the most important parts of implementation. A person’s dignity, privacy and cultural safety still matter, even when a situation is difficult or unsafe.
What happens to the footage?
The policy does not set one simple storage timeframe for body worn camera footage. Instead, footage must be managed in line with WA Health information policies and State Government records rules. In practice, footage linked to a security incident may be kept for longer than routine footage, depending on the type of incident, whether it is needed for investigation, and how the record is classified.
A consumer who wants access to footage involving them will need to contact the relevant hospital or health service and ask about access through Freedom of Information or the appropriate information access process. Access may not be automatic, especially if other people are identifiable in the footage.
Questions consumer representatives can ask
As this policy is put into practice, consumer representatives, Chairs and committee members can play an important role by staying curious and asking practical questions, like:
How will people be told when a body worn camera is being turned on?
How will staff make sure people understand what is happening, especially if they are distressed, unwell, cognitively impaired, culturally unsafe, or communicating in a language other than English?
How often are body worn cameras being activated, and in what kinds of situations?
How will services monitor whether cameras are being used appropriately?
How will consumers, families and carers be able to raise concerns or provide feedback?
How long is footage kept, who can access it, and how are people told about their rights to request access?
How will consumer experience be included in evaluation of the policy?
Keeping people at the centre
HCCWA supports safe health services for everyone – patients, families, carers, staff, volunteers and visitors. We also believe that safety measures must be implemented in ways that protect dignity, trust, cultural safety and compassion.
Many of the situations where body worn cameras may be used will involve people at very difficult moments in their lives. That is why monitoring and evaluation should look beyond compliance and should also consider what body worn camera use means for consumers, including whether people feel respected, informed and safe.
We are sharing this information as part of our commitment to keeping our consumer community informed about policy changes and the work HCCWA is involved in. We hope it supports consumer representatives, Chairs and community leaders to take part confidently in conversations about how this policy is implemented across WA Health.
An essential building block of clinical governance working under the radar.
Individual health advocacy places the person at the centre of care and decision-making about their healthcare. In a busy and highly fragmented health system, independent health advocacy is a critical part of the safety and quality landscape. Health systems are stronger and safer when people are heard, respected and supported in decision-making. The ability to access independent individual advocacy support can help to restore people’s trust in the health system and rebuild their confidence to speak up in future.
Unprecedented increase in need
We are experiencing unprecedented levels of IHAS need for specifically ‘in-the-moment’ advocacy cases from Western Australians.
Category 1 cases aim to be attended to within 24 to 48 hours due to crisis or life altering impact.
January to March 2026 saw an 111% increase in Category 1 cases compared to January to March 2025.
111%
↑ category 1 cases
Our impact by the numbers
Enquiries to our free Individual Advocacy Service
357
Enquiries received from Western Australians Jan to Mar 2026
Increase in enquiries to our service
23%
Percent increase in enquiries Jan to Mar 2025 v.s. Jan to Mar 2026
Voluntary mental health advocacy need
63%
Increase in mental health cases Jan to Mar 2025 v.s. Jan to Mar 2026
CaLD Cases
36%
Increase in cases for CaLD cases Jan to Mar 2025 v.s. Jan to Mar 2026
Referrals from MHAS and HaDSCO Jan to Mar 2026
31%
Referrals from the the Mental HaDSCO and MHAS
Individual Advocate funding
4.8
We can currently fund only 4.8 F.T.E. Individual Healthcare Advocates.
WA leads Australia
Since the 1990s, the WA Government has demonstrated strong leadership by funding Health Consumers’ Council WA (HCCWA) to deliver a free, person-centred and rights-based service across all areas of health and healthcare. This longstanding investment reflects commitment to a community-led model that restores hope, confidence and power to consumers navigating a complex health.
What is independent individual health advocacy in WA?
Skilled independent patient advocates at HCCWA provide one to one support to a wide range of consumers who need support to have their voices heard, or to get answers when things have gone wrong.
HCCWA provides this support
across the state
across all areas of health and healthcare (including voluntary mental health patients)
across all healthcare settings (public, private, primary, hospital, community)
Individual advocacy impact
Upholds people’s health rights
Enables dialogue between patients and clinicians
Helps to repairs relationships between patients and caregivers where they’ve ruptured
Provides solidarity and encouragement
Restores power and confidence that has been diminished by a large and complex system
Enables redress where things have gone wrong
Saves lives
Independent advocacy provides hope to people at their most vulnerable moments.
HCCWA’s Individual Healthcare Advocacy Service Case Studies
Challenging an unjust $1 million medical bill for a family in distress and holding powerful companies to account
A family coming to Australia to live took out the appropriate level of private health insurance for their visa. Unfortunately, the family needed to access a high level of healthcare. While receiving treatment, the family received a call from their insurance company offering them a different policy with a lower premium, to which they agreed. English is not their first language, and no interpreter was offered. This new policy did not cover the care they were receiving, and so the family became liable for a very significant healthcare bill (over $1m). Our Advocate worked with the family and represented them to the insurance company with the result being that the insurance company agreed to pay the healthcare bill.
Advocate intervention addresses a case of unjust billing
An overseas student was billed for a long GP consultation after a brief visit that lasted around 10 to 12 minutes and included a same day referral to a specialist. The higher charge was more than $100 above a standard consultation and could not be claimed through Medicare due to the patient’s visa status, with private health cover already exhausted. After the patient’s attempts to dispute the charge were unsuccessful, our advocate intervened, referencing the correct billing item requirements. Following several communications, the practice acknowledged the error and rectified the account.
End-of-life choice upheld during fast changing circumstances
“HCCWA was contacted by a family who were concerned that their relative’s rapid health decline was not being adequately recognised and responded to during a hospital admission for abdominal pain. The consumer was subsequently diagnosed with a terminal illness. The consumer decided to access Voluntary Assisted Dying (VAD). Given the conditions that need to be met to remain eligible for VAD, and the consumer’s rapidly declining condition, this case was instantly escalated within our advocacy service. The advocate supported the consumer to seek appropriate and timely clinical reviews, clarify decision-making pathways, and uphold their right to seek and receive clear information. HCCWA’s ability to act quickly ensured the consumer’s preferences, rights, and capacity were prioritised at a critical time.
Restoring quality of life after insisting on surgery review and redress
young man in his early 20s with significant and lifelong disability contacted HCCWA after experiencing escalating pain from a complication following surgery. The procedure differed from what had been discussed and consented to, and post-operative follow up outpatient appointment was not provided. Several GP visits, 2 ED visits and four months later, he still had not received post operative follow up and so remained in severe pain; struggling to access appropriate pain management and unable to resume university study or daily life. HCCWA supported him to understand his rights, be heard within the system, and access urgent post operative review by the surgeon and consider complaint or redress pathways if he chooses. He was admitted for surgery 1 working day after our Advocate spoke with the surgeon.
Western Australians who have used Health Consumer’ Council WA’s FREE Individual Healthcare Advocacy Service (IHAS) say:
“She honestly went above and beyond to help me and make sure I understood everything. Also beautiful and caring as well. ”
“Thank you so much for talking with [clinical specialist] and for helping me prep for my consultation with my doctor and attending with me and writing and sending out the notes. I keep referring back to them as I am trying to fill out the paperwork and pay the fees as I get little blips of panic and they are calming and grounding me massively and that’s allowing me room to actually feel excitement about being on the other side of surgery.“
“Thank you so much for all your help and support in this matter. You truly are amazing and very helpful. It is not often these days you find people that go above and beyond to help you and you truly have so thank you so very much from the bottom of my heart.”
“My advocate was excellent in all areas from knowledge, communication and care to me at all times.”
“Thankyou so much for your time today, I called the right person and I appreciate your help and compassion in a free service too, makes me very grateful I’ve got you and your organisation to lean on for support if I need.”
“Many thanks for all of your support – It has been such a help for me as I was truly so overwhelmed I was unable to do anything and it was impacting my wellbeing tremendously. I cannot thank you enough!!”
“Not only did she guide me in the right direction, she also gave me words of moral support and definitely gave me the confidence to continue the tasks at hand.”
Community led, government funded
A powerful partnership that established Australia’s first independent health advocacy service In 1993, the then Minister for Health offered health consumer leaders the opportunity to set up a non-profit organisation to act as an independent voice for health consumers on all aspects of health and healthcare. The intent had been to advocate at a systemic level for the rights and interests of health consumers, patients and families. Yet when this new organisation was featured in the media, the small team were inundated with requests for help from people who needed answers from the health system about individual issues. And so, those staff started to deliver individual health advocacy “because they couldn’t not”.
Increased investment is now required to ensure this “under the radar” service can continue to be there for every day West Aussies
We are in discussions with WA Health about the future of this ground-breaking initiative. After 3 decades, the investment in this service has not kept pace with demand, or with the increased complexity of people’s experiences in healthcare.
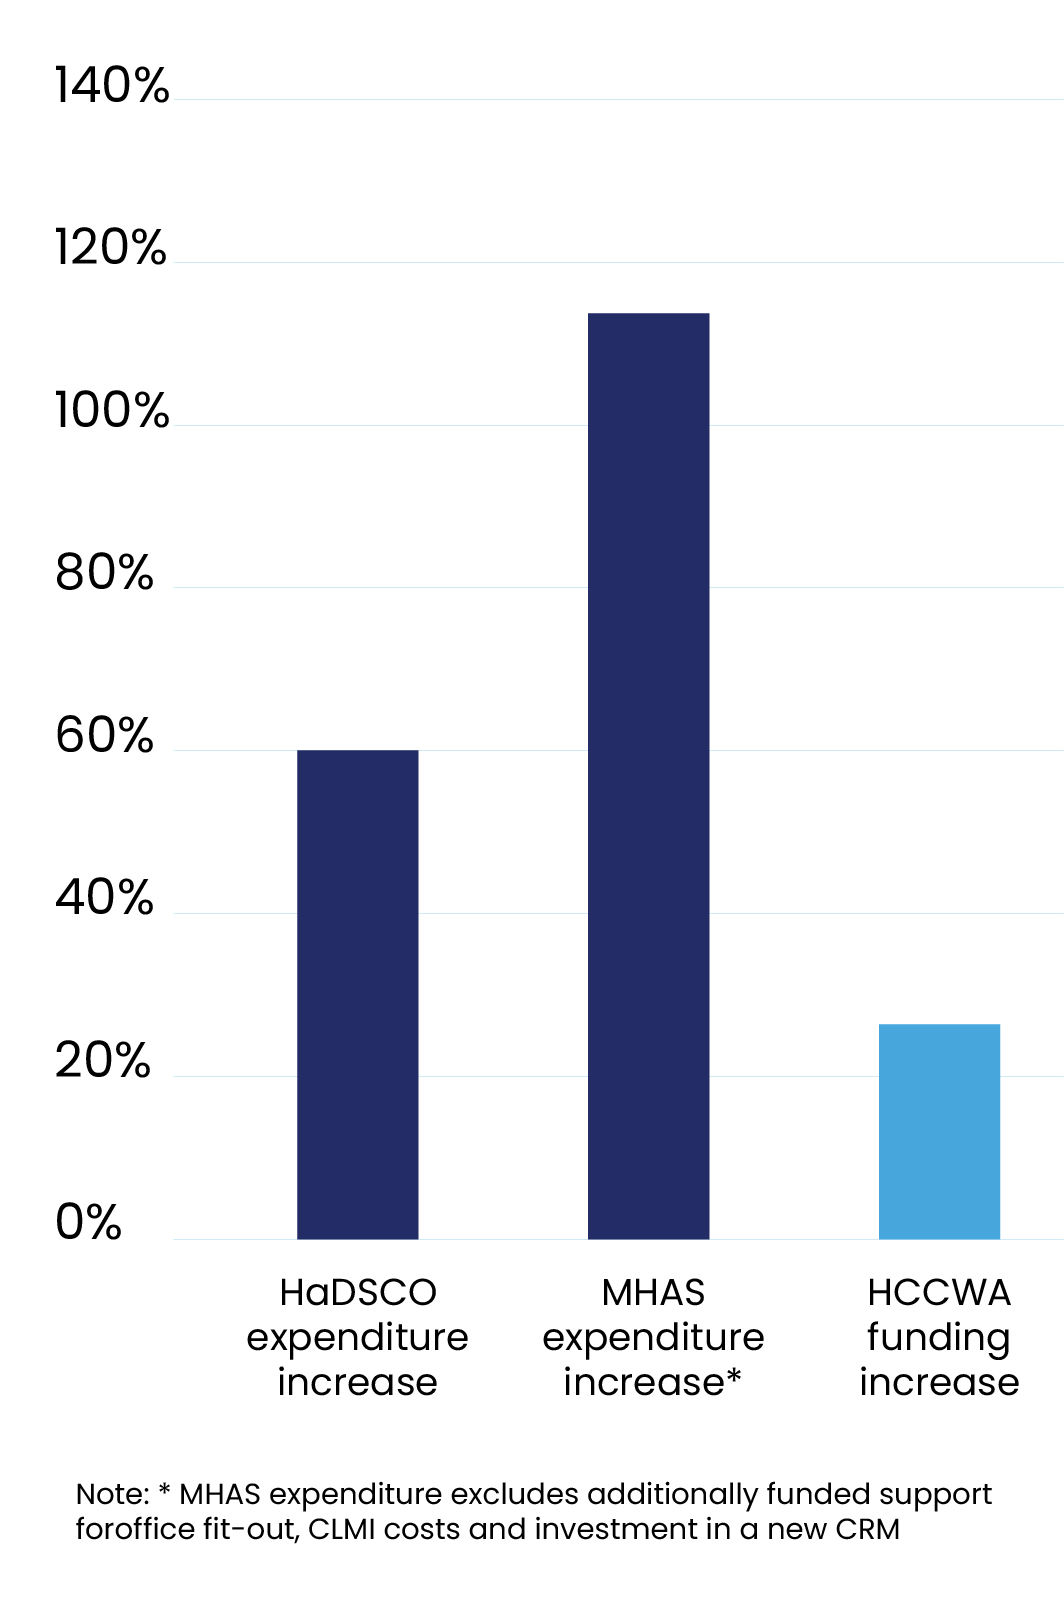
Since the HCCWA budget was last reviewed in 2014, WA Health’s budget has increased by 74%, MHAS expenditure has increased by over 110%, but investment in HCCWA’s capacity has only increased by CPI (27%).
We will be seeking support for a budget business case to ensure that this Australia-first program can continue to play its part in the continuous improvement of the health system, and ensure that Western Australians can continue to be heard, respected and supported.
As a minimum, we want to be able to be there for anyone who is involved in a serious clinical incident WA. We estimate that this requires an increased annual investment of $1.9m.
Shifting the dial on patient safety – on-site patient advocates, strengthening consumer voices
Internationally, evidence suggests that approximately 10% of healthcare causes harm. One contributor to this is patients and families being dismissed when raising concerns in a clinical setting. In a busy healthcare setting, patient concerns can go unheard. We believe on-site patient advocates – independent of the WA Health system – would significantly strengthen patient and family voices, enabling their voices to be heard alongside the clinical experts.
This would require a significant phased investment and we would welcome the opportunity to be involved in shaping how this might look for WA.
For further information about this report please contact Health Consumers Council WA on 08 9221 3422 or info@hconc.og.au
To discuss any of the content, please contact Clare Mullen, Executive Director at CEO@hconc.org.au
Health Consumers’ Council WA’s latest Systemic Advocacy Report highlights how consumer and community voices are helping shape health policy, services, and system reform across Western Australia. Covering January to March 2026, the report outlines HCCWA’s work across preventative health, referral pathways, consumer engagement, rural access, Aboriginal health, mental health, and informed decision making.
During this period, HCCWA contributed to policy submissions, Ministerial roundtables, committee governance reviews, and national reform discussions, while continuing to bring lived experience perspectives into high level decision making. The report also highlights advocacy on outpatient access, informed financial consent, consumer rights, and the need for more inclusive and community-led approaches across the health system.
The report reflects HCCWA’s ongoing commitment to ensuring healthcare policy and reform are shaped by the experiences of patients, carers, families, and communities across WA.
Acknowledgements
We acknowledge Aboriginal and Torres Strait Islander peoples and communities as the Traditional Custodians of the land we work on, specifically the Whadjuk people of the Noongar nation, and pay our respects to Elders past, present, and emerging. Australia always was and always will be Aboriginal land.
Health Consumers’ Council acknowledges the unique insights and strength of those who navigate the complexities of the health system as consumers and thank them for sharing their lived experience and wisdom to help make healthcare fair for everyone.
In this report we provide our members, friends and stakeholders with an update on how we’re amplifying and championing diverse consumer and community interests to help drive positive change across the health and social care sectors in WA.
During this period, HCCWA continued to influence policy, strengthen partnerships, and elevate consumer and community voices across the health system.
Our reach and engagement
Contributed to 5+ policy submissions and strategic consultations
Engaged with state and national government agencies, Ministers and MPs
Participated in 10+ committees, advisory groups, and sector forums
Delivered 3 sector presentations and panel contributions
Contributed to media coverage on key consumer health issues
Key areas of influence
Preventative health policy and whole-of-government approaches
Access to care, including referral pathways and rural primary care
Consumer engagement and lived experience in system design and governance
Equity in health care, including Aboriginal health and community-led approaches
Transparency and informed decision making for consumers
Highlights from this period
Provided strategic input to the WA Department of Health Capability Review, strengthening the focus on consumer and community partnership
Contributed to national policy discussions on modernising referral pathways, advocating for improved access, transparency, and informed choice
Supported Ministerial roundtables on preventative health, bringing forward consumer priorities including early years, social determinants, and community-led approaches
Facilitated engagement between Aboriginal Elders and the Minister for Health and Mental Health, elevating community perspectives on research and program design
Shared insights across sectors, including presentations to the WA Country Health Service and the Community Relief and Resilience Network
This work reflects HCCWA’s ongoing role in ensuring that consumer and community voices inform policy, shape services and contribute to a more equitable and responsive health system.
How systemic advocacy is organised at HCCWA
This period we said farewell to Bronwyn Ife, HCCWA’s Systemic Advocacy Lead, who returned to a role in local government. As the fixed term funding that covered the Systemic Advocacy Lead role is not ongoing we will not be replacing that role. Due to funding constraints, HCCWA’s systemic advocacy work is undertaken by members of the Leadership team alongside their other responsibilities.
Do you find this information valuable?
This is a new publication for us, and we’d welcome feedback – what is helpful/interesting? What is not?! Let us know by emailing us at engagement@hconc.org.au
HCCWA was approached as a key stakeholder to provide input to inform the Capability Review of the WA Department of Health. These reviews are carried out by the WA Public Sector Commission as “a permanent, ongoing mechanism to lift the capability of the public sector and drive performance improvement”. HCCWA’s feedback covered WA Health’s approach to partnering with consumers and the community.
HCCWA was approached for preliminary feedback about proposals to review specialist titles in dentistry. HCCWA’s feedback was:
The language and formatting of these consultation materials is very complicated and likely to be challenging for most consumers/community members – unless they’re very experienced consumer representatives, or work for a consumer organisation.
This is a very important topic – we know that some of the harm that’s been experienced by consumers in recent high profile cases is due to the lack of clarity about the different abilities of general dentists and prosthodontists
Ahpra and the Dental Board should seek targeted input from consumers across the country
Attention should also be paid to how consumers are informed about these distinctions, how consumers can be sure they’re being treated by someone with the appropriate skill level and qualifications, and how they can make informed choices about which health professional they choose to be treated by.
We highlighted the benefits of hospices and the important role they can play in supporting patients and families both in the community as people live with life-limiting conditions, and at end of life.
We highlighted the importance and value of the Compassionate Communities approach, including the evidence about their value in reducing hospital use from the South West: research from 2023 showed lower hospitalisations, less hospital days/month, and less emergency presentations https://journals.sagepub.com/doi/epub/10.1177/26323524231205323)
Australian Department of Health, Disability and Ageing
This consultation sought the views of patients, medical providers and other interested parties on whether current Medicare referral arrangements are effectively supporting access to specialist care. It also seeks views on suggestions for reform.
HCCWA provided this feedback:
The current referral process does not make it easy for patients to access specialist care
Including cost information and links to Medical Costs Finder on referrals would help patients make more informed financial decisions
Patients should be able to switch specialists under the same referral without needing a new referral
Our GPs should be kept informed about our treatment with the specialist throughout the duration of the referral – if that is what we want
The lack of information available to consumers to make truly informed decisions about their preferred referral options could be a barrier to the take up of an Australia-wide digital referral process.
There is almost no information consumers can use to determine the quality of care they might receive for any particular clinicians. For communities who are often served by overseas trained doctors, their treating doctor may not have any knowledge or pre-existing relationships with other clinicians to inform their recommendation.
This could be addressed by requiring clinicians to publish information about any complaints they receive (noting that not all consumers have the emotional energy to go through the administratively heavy Ahpra notification process). Or to strengthen the Ahpra annual registration process to require evidence of consumer feedback in some way. While google reviews may be inadequate, they are sometimes the only publicly available information for consumers to use as they try to make an informed decision.
It is important that consumers are able to access neutral information about things to consider when looking for a specialist. The “service” is highly technical, and the “market” is diffuse and confusing to navigate. There’s a risk that “good bedside manner” could become the standard for decision making in the absence of consumers being able to access other information about other quality measures they could consider.
That any policy should be supported by significant investment in ensuring consumers are supported to make fully informed decisions. For example, all referrals could be required to include mandatory wording directing consumers to online information about how to make a decision, and what questions to ask about their options.
Information about making informed decisions should be co-designed by consumers, and could be included in consumer-led training delivered by consumer organisations.
Recent media accounts – Four Corners – have made it very clear that our healthcare system cannot be based on doctors policing themselves. While many are trustworthy people who deliver high quality care, it is clear that where this is not the case, the consumer has little hope of receiving honest feedback about colleagues from their own doctors.
Mandating the provision of information in plain language that has been written by consumers for consumers that outlines the process, their rights, and what they can expect – i.e. informed financial consent – and where to go if they have questions could improve patient understanding of referral arrangements. This could be on a website – similar to the Choosing Wisely program.
The ability for patients to seek a second opinion from a new specialist under the same referral would be enormously beneficial for patients. In the current “market” consumers are significantly disadvantaged and disempowered by limited access to information on which to base their decisions. Being able to access a second opinion is likely to have a significantly positive impact.
If were to be coupled with powerful AI-powered consumer healthcare decision tools, this will be a game-changer in terms of re-empowering consumers.
HCCWA was one of the signatories to a letter seeking an update on the implementation of the recommendations from the Statutory Review of the Mental Health Act 2014 (WA) that was completed in 2024.
As background, HCCWA contributed to the Review in 2021 by hosting consumer consultations on the experiences of people accessing mental health services on a voluntary basis. We look forward to being able to share how these recommendations are being implemented with our community.
HCCWA was asked to review draft guidelines for WA Health staff on establishing and running committees.
Our feedback related to how to ensure that including consumer, community and lived experience voices in WA Health committees was a valuable experience for everyone.
HCCWA’s Executive Director, Clare Mullen, took part in a Leadership Discussion Circle with a group of WA Country Health Service leaders, sharing HCCWA perspectives on partnering with consumers at all levels of decision making.
Clare Mullen presented to the Community Relief and Resilience Network on key health consumer issues, contributing a consumer perspective to discussions across the emergency relief sector.
The Community Relief and Resilience Program provides policy representation and sector support to Western Australia’s emergency relief sector. These services support individuals and families experiencing poverty or financial stress through food and material aid, financial assistance and referrals to other support services.
There are more than 300 agencies across WA delivering community relief, ranging from small volunteer-run services to large multi-program organisations.
Tania Harris, HCCWA’s Engagement Manager, Aboriginal and Torres Strait Islander Lead and Disability Lead, took part in a panel discussion that brought together perspectives from research, consumer advocacy, clinical practice, innovation and policy.
The panel explored whether current policy, funding and service delivery frameworks are fit for purpose and effective in translating diabetes innovation into equitable care with HCCWA contributing a consumer and lived experience perspective to support more inclusive and responsive approaches.
The Hon Sabine Winton MLA, Minister for Preventative Health
HCCWA attended four preventative health roundtables at the start of 2026:
Mental Health and Early Years Wellbeing
Health Promotion
Screening and Genomics
Immunisation
Across all of these sessions we shared what we hear from consumers, carers, family and community members:
Need to address the social determinants of health, particularly poverty/low-income
A focus on first 1,000 days and healthy families is essential – particularly preventing and addressing early childhood trauma
A lot of prevention takes place outside the “health system”; Government needs to be joined up in its approach
There is a need for more community-driven/community-led health promotion activities at a place level
Need much more involvement of a wide range of consumers, carers, families and people with lived experience in all scoping, planning, delivery and evaluation of initiatives
Targeted work should be done to include the voices of people who may not engage in traditional “consultations”, including people experiencing homelessness, people with intellectual disability, and people where English is not their first language
The value of peer-led approaches across all areas of health and mental health – including in health promotion activities within and outside clinical settings
The Hon Meredith Hammat MLA, Minister for Health and Mental Health
HCCWA supports the Healthy Lifestyle Program’s consumer engagement and directly supports and facilitates the Healthy Lifestyle Program Cultural Advisory Group and its members (the Elders). The group is made up of respected Aboriginal Elders who have decades of experience supporting researchers and research projects.
The Elders were concerned about the impact of short-term research pilots on their families and communities. They requested the opportunity to meet with senior decision makers to share their and their communities’ perspectives and experience with the research pilot pathways.
Minister Hammat and her team met with the Elders in March 2026 and welcomed the opportunity to hear about the program and their experience.
Since 1994, Health Consumers’ Council WA has been advocating for the interests of the WA community, health consumers, patients, carers, and families when it comes to health and healthcare.
HCCWA will continue to work across government, the health system, and the community to ensure that consumer voices shape policy, services, and system reform. This work remains critical to building a more equitable, responsive, and person-centred health system in Western Australia.
For further information about this report please contact Health Consumers Council WA on 08 9221 3422 or info@hconc.og.au
To discuss any of the content, please contact Clare Mullen, Executive Director at CEO@hconc.org.au
WA is the first state to have a Minister for Preventative Health, the Hon Sabine Winton. Late last year, Health Consumers’ Council WA was invited to be part of a number of roundtables gathering input to inform the development of WA’s first preventative health strategy.
There were six roundable discussions and HCCWA were invited to attend four:
Mental health and wellbeing in the early years
Immunisation
Health promotion
Cancer screening and genomics
The other two were:
Sexual health
How government departments work together on this agenda
A number of other consumer and community organisations attended some of the sessions including Alcohol and Other Drug Consumer and Community Coalition, WA Association for Mental Health and Aboriginal Health Council WA.
HCCWA’s input to these discussions was based on the deep and broad understanding of health consumer interests which comes from our daily interactions with patients, families and carers, people with lived experience and community members. In general our input was:
It’s critical to address the social determinants of health – particularly poverty.
A focus on the first 1,000 days and healthy families is essential – we highlighted the need to have a concerted focus on preventing and addressing early childhood trauma
A lot of prevention takes place outside the “health system”; Government needs to be joined up in its approach, and move to being more community-centred, and less “service-centred”
There is a need to invest in more community-driven/community-led health promotion activities at a grassroots level
Unsurprisingly we called for much more involvement of a wide range of consumers, carers, families and people with lived experience in all scoping, planning, delivery and evaluation of all preventative health initiatives
Targeted work should be done to include the voices of people who may not engage in traditional “consultations”, including people experiencing homelessness, people with intellectual disability, and people where English is not their first language
The value of peer-led approaches across all areas of health and mental health – including in health promotion activities within and outside clinical settings.
The Minister sat in the room for the duration of each session and I had a clear sense she’d listened deeply and took the feedback on board. She also made reference to a public facing consultation process – we’ve flagged with her office that we’d like to work with them to ensure wide and deep engagement.
We’ll circulate more information about the public consultation when we get it. Clare Mullen, Executive Director
WA Health is introducing a new Electronic Medical Record (EMR) across public hospitals and health services in Western Australia.
This is the largest clinical and digital transformation WA Health has ever undertaken, and a once-in-a-generation opportunity to improve how care is delivered across the state.
An EMR is a secure digital version of your health record. It brings together information about your care in WA public hospitals – such as test results, medicines and treatment plans – so clinicians can access the information they need to support your care, when they need it. It also includes smart clinical features, such as alerts for allergies or medicine interactions, that help support safer care.
The EMR will also include a portal for patients. The intent is to provide a secure online tool that could, over time, offer access to selected health information (such as parts of a health record, appointments and results) and support people to be more involved in their care and in supporting their family members. Final features and timing will be determined as the program progresses.
What this means for consumers and carers
For consumers and carers, the EMR is intended to support care that feels more joined-up and consistent across WA. It can reduce the need to repeat your story, help avoid delays caused by missing information and support safer care by helping clinicians spot important information sooner. It will also make it easier to access your own health information.
Why we’re asking for consumer input now
The EMR Program has been working closely with the Health Consumers’ Council and the EMR Program Consumer Reference Group for some time to establish strong foundations for consumer input into the Program. This work has helped shape how consumers are involved and has informed key principles around safety, equity, privacy and trust, including the development of the EMR Program’s Consumer Charter. As the Program moves into more detailed decision-making, it is now important to broaden consumer involvement and build a large, diverse pool of consumers who can contribute across different areas of care. This helps ensure decisions reflect the experiences of people with different health needs, backgrounds and interactions with the WA health system. The EMR Program is currently working through important decisions about how care is delivered across WA, including where it makes sense for things to be done in the same way everywhere. To support this, the Program is setting up a number of Clinical Advisory Groups, working groups and committees. These are groups of clinicians and other experts who look at specific areas of care and help guide decisions about how the EMR should support safe, high-quality care across the system. Many of the topics these groups consider affect how people experience care in real life – for example, how care teams work together, and what it’s like to move between hospitals and services. Because these decisions will shape how care works for many years to come, it’s important they are informed by the experiences of patients, carers and families. Your input helps ensure decisions are grounded in what actually works well, what’s difficult, and what could be improved, so care can be delivered more consistently and in ways that better support people across WA.
About the Expression of Interest
We are seeking Expressions of Interest (EOI) from individuals who are experienced in representing consumer perspectives to join a pool for the following roles:
Standing member of an EMR Clinical Advisory Group (CAG), or other relevant committee or working group
Participation in short-term or topic-specific meetings, where your lived experience or expertise is particularly relevant.
The Expression of Interest Form highlights the different clinical focus areas we may need input on, and you can nominate up to five.
Who we’re looking to hear from
We are seeking people of different ages, cultural backgrounds and life experiences, people living in metropolitan, regional and remote areas, carers and family members, and people with experience of different health services and conditions. Having a wide range of perspectives helps ensure the EMR works well for the many different people who use WA Health services.
You don’t need any technical knowledge. What matters is your experience of care as a patient, carer or family member, and your willingness to share that experience in a way that helps improve care for others.
Time Commitment: Some people may be invited to join a Clinical Advisory Group with a regular (likely monthly) commitment, while others may be invited to take part in short-term or topic-specific discussions where their experience is particularly relevant. The Program is still evolving, so topics, timing and levels of involvement will vary. Commitment expectations will be discussed in advance of your appointment.
Support: Consumers can elect to receive additional support before, after and between meetings. This may include pre- and post-meeting briefings and cross-committee meetings to access peer support and learning. The Program will consider reasonable adjustments to support accessibility, communication and participation needs, and encourages consumers to discuss any barriers or support needs with the HCC team.
Online/ in-person attendance: Most meetings will be held online and are designed to be accessible using common devices. If access to technology or confidence using online tools may affect your ability to participate, please contact HCC to discuss available support or reasonable adjustments.
Consumer participation payment: Participation is paid in line with agreed consumer payment arrangements ($75/hour for consumer advisory roles and $37.50/hour for consumer representative roles), with details provided before any involvement is confirmed.
What happens after you submit an EOI
Everyone who submits an EOI will receive an acknowledgement. EOIs will be reviewed to identify people whose experience and interests best match current and upcoming opportunities.
Some applicants will be invited to a short, informal conversation so we can better understand their experience, availability and any support needs. These conversations are not formal interviews – they’re about getting to know you and working out how and when involvement might be a good fit.
Not everyone who submits an EOI will be invited to a conversation at this stage. This doesn’t reflect the value of your experience – it simply reflects current Program needs and timing.
There will be further waves of recruitment as the EMR Program continues, and people who are not contacted in this round may be considered for future opportunities.
How to apply
If you would like to submit an EOI, please complete the online form using the link below. Please allow 15-20 minutes to complete the form.
If you need any assistance or support to complete this EOI, please contact HCCWA on 08 9221 3422 or emr@hconc.org.au
Please complete the EOI at your earliest convenience. The first round of committee appointments is expected to occur February and March 2026.
Health Consumers’ Council WA (HCCWA) welcomes today’s announcement by the WA Government of increased investment in hospital capacity, recognising it as an important step in responding to the current demand for hospital care.
HCCWA Executive Director Clare Mullen said the investment would be reassuring for people struggling to access timely care, and emphasised that the ultimate goal must be a healthier population that requires less hospital care in the first place.
“Every Western Australian deserves access to high-quality hospital care when they need it —but a truly sustainable health system keeps people healthy and supported before they reach crisis point,” Ms Mullen said.
“No one wants to need hospital care. Ill-health need not be inevitable. To reduce pressure on hospitals, we need to invest just as strongly in prevention, early intervention, and the social conditions that keep people well.”
Ms Mullen said consumers consistently raise concerns about the difficulty of accessing affordable and timely primary and community care and early intervention with health issues —particularly for people living with or at risk of chronic conditions, or in regional and remote areas.
“When there is a lack of early intervention programs, or people can’t access the right care at the right time, health problems escalate and hospital admissions become inevitable,” she said.
“It’s a relief to see hospital expansion to ease the current pressure on services. But without strong community-based options, as well as targeted investment in preventative health activities, the demand for acute care will keep rising.”
“Western Australians want to see a system that supports health, as well as one that treats illness — one that helps people to stay well, connected and supported in their communities.”
HCCWA is calling for a balanced approach that includes:
Long-term investment in early intervention and preventive health programs,
Better funding for community-based and multidisciplinary care, and
policies that address the social and economic drivers of poor health.
“This is a welcome and necessary investment in hospital capacity. And we look forward to partnering with WA Health to ensure consumers and community members are actively involved in shaping these important infrastructure projects,” Ms Mullen said. “And if we want fewer people needing hospital care, we must also invest in prevention.”
Right now, health services are under pressure around the world. In this LinkedIn post an ED doctor in the UK shares his perspectives on why people might be experiencing long waits in Emergency Departments.
Need healthcare that can’t wait?
If you’re seeking healthcare which is unplanned but is not an emergency or life-threatening – and it can’t wait until you can get an appointment with a GP – there are a few options that don’t require you to sit for a long time in an Emergency Department:
Call HealthDirect or visit the website for advice and information 24/7 – this service has been significantly improved in recent years and includes the option to discuss your symptoms with a registered nurse.
Medicare Urgent Care Centresare free at the point of care – you can find your nearest online at https://www.health.gov.au/find-a-medicare-ucc or by calling HealthDirect on 1800 022 222
You may be able to walk-in, or need to make an appointment – check with the centre closest to you
Other urgent care centres – such as those provided by St John Health – provide urgent care without an appointment with a fee to be paid.
You will need to pay up-front but Medicare Card holders will get a Medicare rebate.
The up-front costs can range from $168 Monday to Friday to $310 on public holidays
The out of pocket costs (after the rebate) range from approx $125 Monday to Friday to $175 on public holidays
Emergency or life-threatening illnesses or injuries require immediate medical attention by an emergency department or hospital. For example, things like chest pain, breathing difficulties, severe burns, poisoning, loss of feeling, and seizures.
The Federal Minister for Health recently encouraged Australians to stay up to date with COVID vaccines – you can find out more, including where to access a vaccine free of charge at https://www.healthdirect.gov.au/covid-19-vaccine-faqs
Maintain good health hygiene habits
if you’re unwell, reduce the chance of infecting others by staying home, wearing a mask if out in public, and wash your hands regularly
and in particular, take action to reduce the chance of infecting older people in your community or family
pay attention to air quality in homes and buildings
HCC’s advocacy in this area
At HCCWA we are actively advocating for the interests of health consumers including patients, carers and family members in relation to ensure affordable access to healthcare across primary, community and hospital settings. This includes providing input on the WA Government’s work in relation to virtual care, care for older people, and emergency access.